
The short answer. OVA Solutions develops medical devices from the first requirement to a design your contract manufacturer can build: electronics, firmware, mechanics, prototypes and design transfer, run by one team under the group’s ISO 13485:2016 certified quality system. Our 62 engineers have developed 220 medical devices since 2015, from wrist monitors and rehabilitation aids to a portable ventilator. We charge $125 per hour and agree the budget and timeline for each phase before the work starts.
What we do
A medical device needs four engineering disciplines on one schedule: electronics, firmware, mechanics and test. We keep them in one team and one plan, so a change in one discipline is checked against the others before it becomes a problem in verification.
Requirements and architecture
User needs, intended use, design inputs, system architecture, risk inputs and a phase plan with hours and a ceiling. On one rehabilitation equipment program discovery took about 280 engineering hours.
Electronics
Low-noise front ends for ECG and EEG, battery, charging and power paths, BLE, Wi-Fi and cellular radios, defibrillation and ESD protection, multilayer and rigid-flex boards.
Firmware and embedded software
Firmware on STM32, nRF and ESP32 microcontrollers with FreeRTOS or Zephyr, Yocto Linux on i.MX processors, BLE stacks, update mechanisms and test software, under an IEC 62304 software life cycle.
Mechanical and industrial design
Enclosures, mechanisms and fluid paths, finite element and stress analysis, materials for skin contact, and design for injection molding and assembly.
Prototyping and test
Digital prototypes and simulation, 3D-printed and machined parts, board spins, test stands and robotic test rigs, and batches of up to 200 units built in house.
Design for manufacturing and transfer
Bill of materials with second sources, test points and end-of-line fixtures, work instructions, pilot build support and process validation with your contract manufacturer.
We work with founders who need a first device to show investors and with established manufacturers who need a redesign, a firmware port or a production transfer. Read more: medical device development for startups and engineering for established manufacturers.
Device areas we know well
Wearables and remote monitoring
Wrist monitors with cuff blood pressure, skin-worn patches, knee and gait monitors, stimulators. In mid-2026 about 30% of our ongoing projects were wearables.
Orthopedics and rehabilitation
Load-sensing crutches, range-of-motion and gait monitors, post-operative therapy devices, powered rehabilitation equipment and fixation tools.
Neurotechnology
EEG acquisition boards, a wearable controller for a sensory-restoration neural implant, and neuromuscular stimulators.
Respiratory and critical care
A portable battery-powered ventilator built from ten boards: respiratory control, oxygen and air mixing, capnography, battery management and user interface.
Therapy devices
Post-operative cold therapy, wearable muscle stimulation, focused-ultrasound hyperthermia for tumor heating and a warm-vapor device for dry eye.
Surgical and hospital equipment
Electronics, firmware and an NFC reader for a multi-specialty surgical robot, an endoscopic suturing system, a cranial fixation tool and medical carts.
Selected projects
All projects are described without client names. Full write-ups are in our case studies.
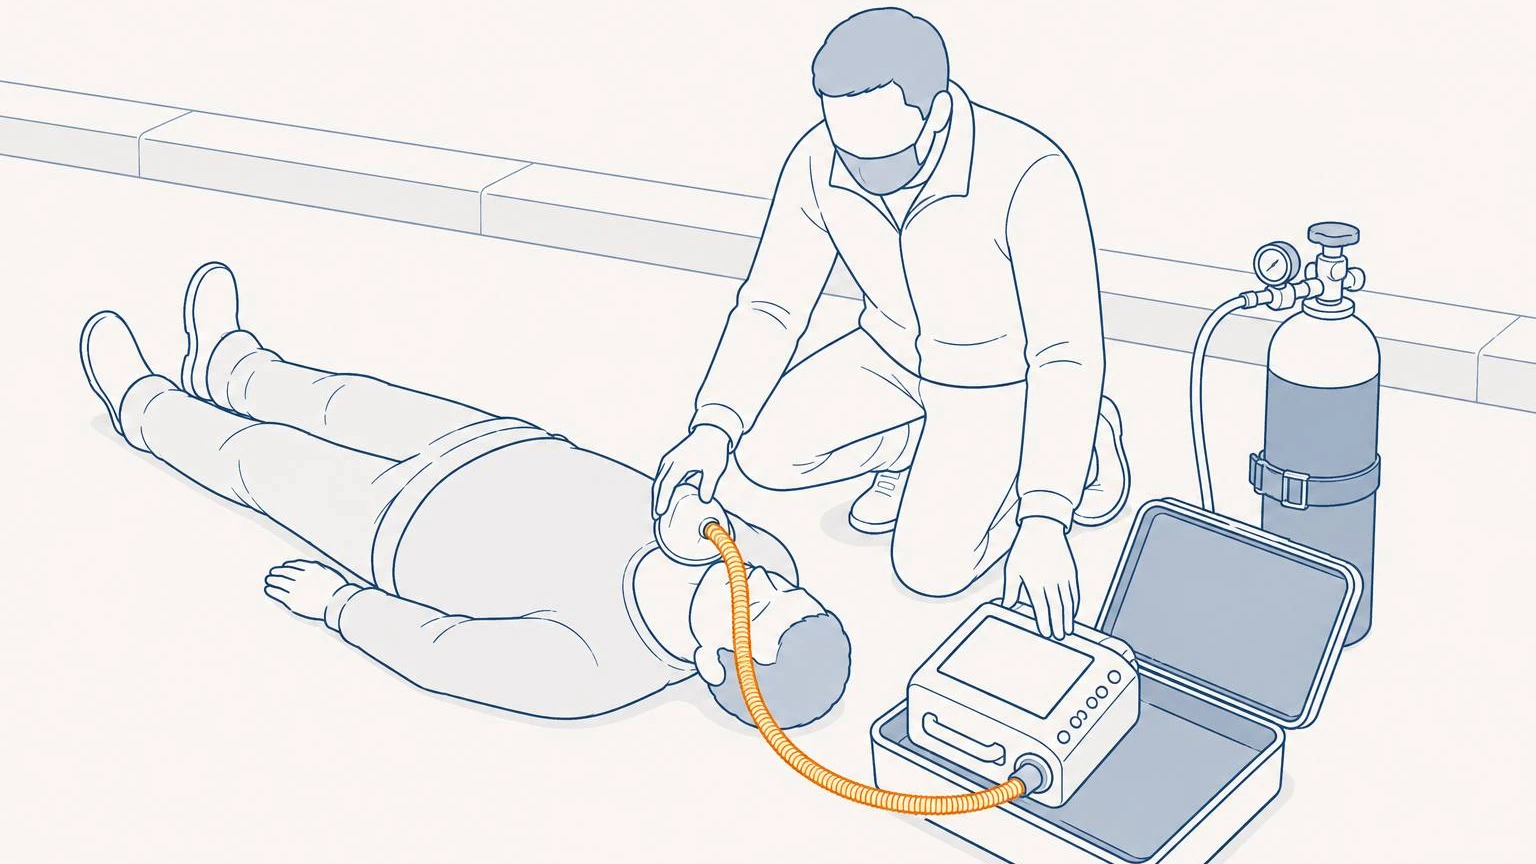
Portable ventilator, ten boards
Boards split by hazard boundary so the user interface could change without reopening verification of the respiratory control.
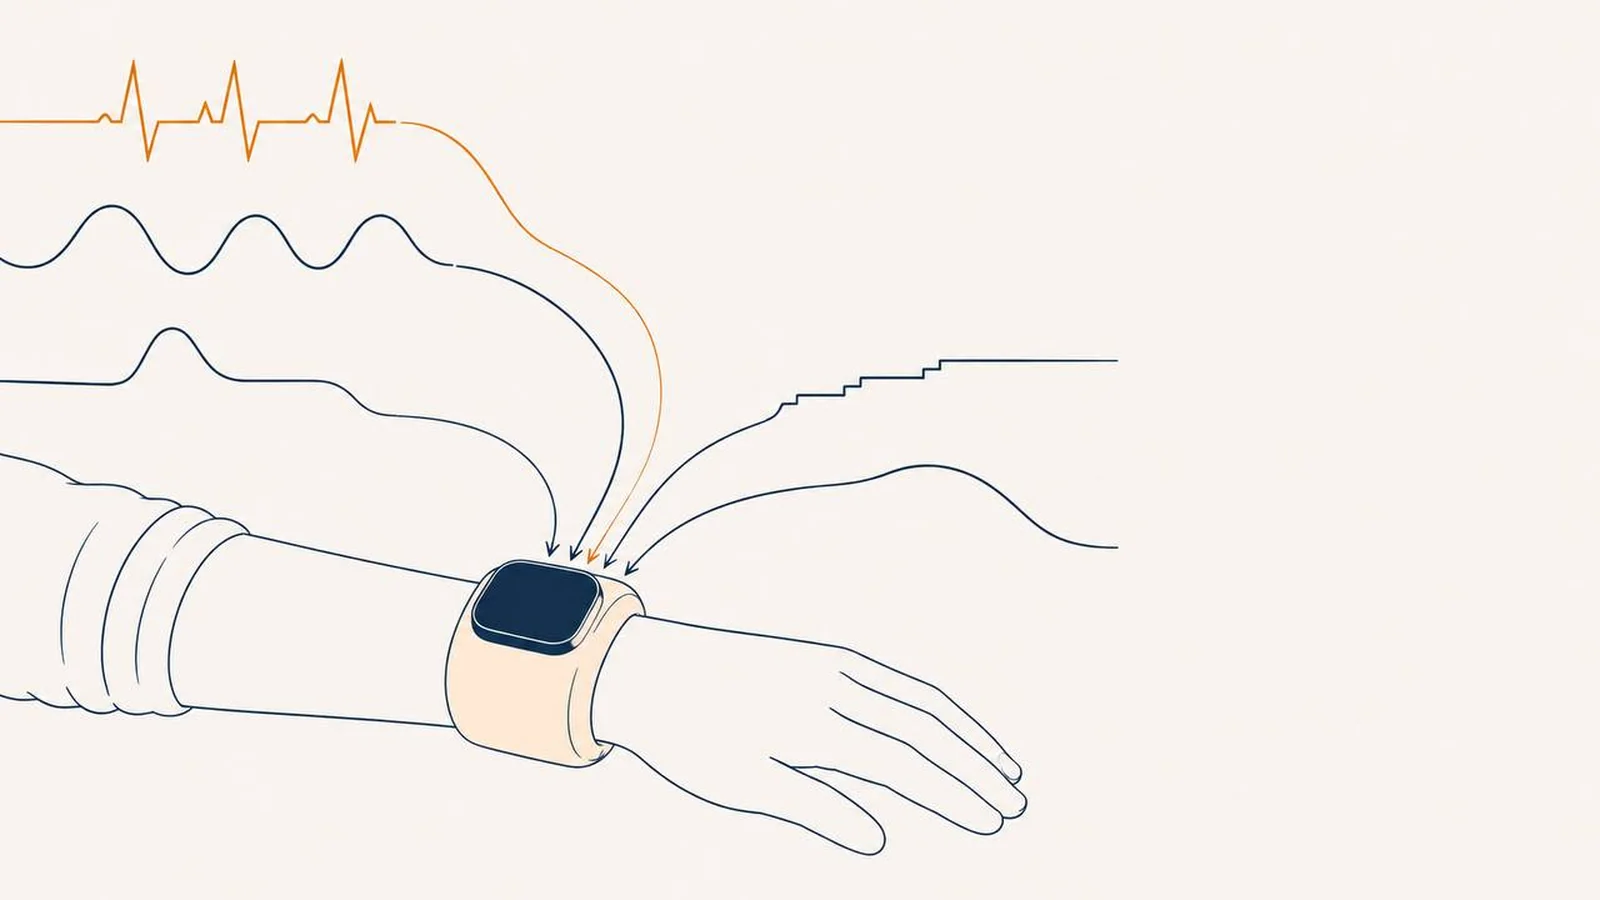
Wrist monitor with cuff blood pressure
Five vitals on one wrist, with the measurements scheduled so the cuff pump does not corrupt ECG and SpO2.
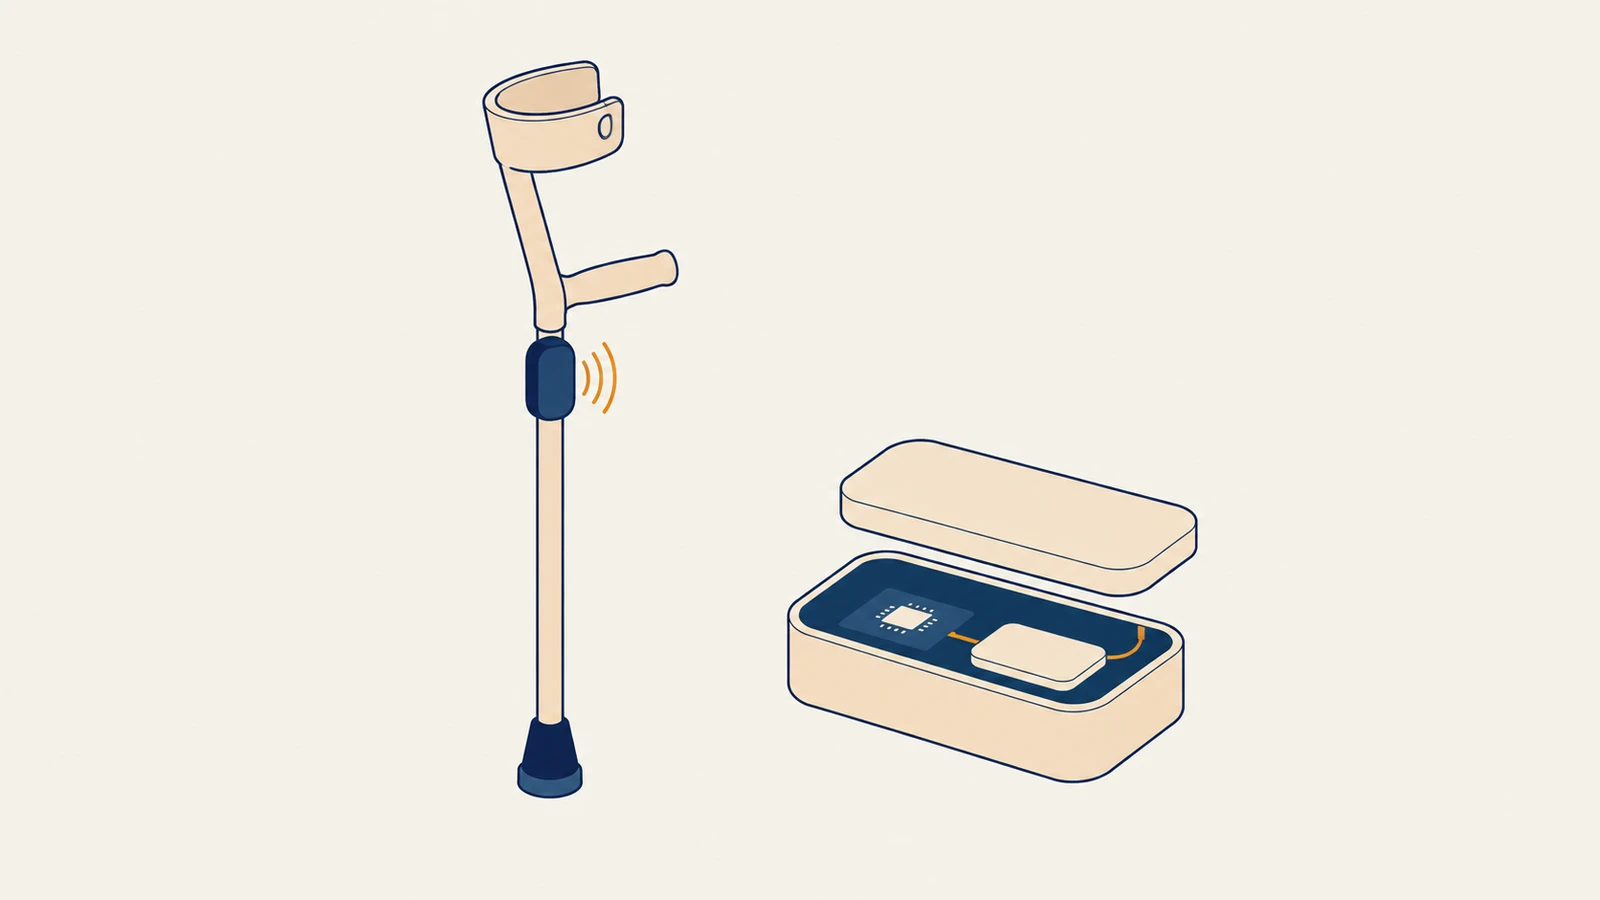
Load-sensing rehabilitation crutch
Load sensors, BLE and an injection-molded housing; 100 pairs produced.
Glucose monitoring patch for a pharma company
Eight phases from discovery to a clinical-ready prototype now in clinical trials, including a 100-unit batch and support during the clinical study.
How a program runs
Discovery
Requirements, users and use environment, intended use, architecture options, risk inputs, and a plan with hours per phase. The plan becomes the budget ceiling in the contract.
Proof of concept
Answer the riskiest physics question first, often with digital prototypes and simulation before any hardware. On one blood-handling device we compared 10 digital prototypes and built the best three.
Design
Electronics, firmware and mechanics in parallel, with safety-critical subsystems frozen first. On the portable ventilator the respiratory control and gas mixing boards were locked while the user interface was still changing.
Prototypes and golden sample
Functional prototypes that look and behave like the production device, then a golden sample: the pre-certification unit that fully meets the functional requirements and becomes the reference for production.
Verification support and clinical builds
Bench testing, test software, devices for preclinical and clinical studies, and support during the study. On a glucose monitoring program the clinical phase took about 2,000 engineering hours and about 30 devices.
Design for manufacturing and transfer
Second sources for critical parts, test strategy and fixtures, work instructions, pilot build and process validation with the contract manufacturer. For an average product this takes 2,500 to 4,000 engineering hours.
Post-production support
Component changes, supplier issues and small redesigns once the device is in production, usually 200 to 400 engineering hours a year.
However, once you have a decent plan in the beginning, you can commit to the timeline. You can commit to the budget. So, the budget is firm. The timeline is firm.
Hours and budgets
Lisa Voronkova described the typical size of a project in hours on the Global Medical Device Podcast in September 2026. Multiplied by our rate, the ranges look like this:
| Project | Engineering hours | At $125 per hour | Duration | What it usually is |
|---|---|---|---|---|
| Small | 2,000 to 3,000 | $250,000 to $375,000 | Half a year to a year | Clear architecture built on proven technology |
| Mid-size | 5,000 to 6,000 | $625,000 to $750,000 | About a year, team fully loaded | Mechanics, electronics and firmware together, for example drug delivery or diagnostics |
| Large | 10,000 to 30,000 | $1.25 million to $3.75 million | 12 to 16 months and more, plus clinical and regulatory work | Surgical robotics, a ventilator, glucose monitors |
| Design for manufacturing | 2,500 to 4,000 for an average product | $312,500 to $500,000 | After the prototype phases | Industrialization, test fixtures, pilot build, process validation |
| Post-production support | 200 to 400 a year | $25,000 to $50,000 a year | While the device is produced | Component changes, supplier issues, small redesigns |
Two real projects for scale:
| Project | Hours | Duration | Engineering cost | Deliverable |
|---|---|---|---|---|
| Electronics and firmware for a rehabilitation chair | 2,100 | 16 weeks | $260,000 | Five pre-production units and a design history file ready for a 510(k) submission |
| Glucose monitoring patch for a pharma company | 11,600 | 1.5 years | About $1.5 million plus $20,000 to $40,000 of materials | A clinical-ready prototype, now in clinical trials |
So, for context, median path for a new Class II device from concept to 510(k) is around three million and thirty-one months according to the statistic that I see in the market.
More on pricing, FDA fees and how to compare quotes: what medical device development costs.
Standards we design and document to
We design and document to the standards below. Accredited laboratories run the formal tests, and the manufacturer declares conformity and holds the regulatory responsibility.
| Standard | What it covers | Current edition, October 2026 | What is changing |
|---|---|---|---|
| IEC 60601-1 | Basic safety and essential performance of electrical medical equipment | Edition 3.2 (2005 + A1:2012 + A2:2020) | Edition 4 is split into 12 drafts; publication forecast 2029 to 2031 |
| IEC 60601-1-2 | Electromagnetic compatibility | Edition 4.1 (2014 + A1:2020) | No new edition in development |
| IEC 60601-1-11 | Home healthcare environment | Edition 2.1 (2015 + A1:2020) | No new edition in development |
| IEC 62304 | Software life cycle | Edition 1.1 (2006 + A1:2015) | Edition 2, retitled for all health software, is a committee draft; forecast 2028 |
| IEC 62366-1 | Usability engineering | Edition 1.1 (2015 + A1:2020) | Companion report 62366-2 becoming a technical specification, forecast 2027 |
| ISO 14971 | Risk management | 2019, reconfirmed in 2025 | Guidance ISO/TR 24971 marked for revision in July 2026 |
| ISO 10993-1 | Biological evaluation | 2025 (6th edition, published November 18, 2025) | FDA recognized it in part on May 25, 2026; the 2018 edition is accepted until July 1, 2029 |
| IEC 62133-2 | Lithium-ion cells and batteries | Edition 1.1 (2017 + A1:2021) | Edition 2.0 forecast for 2027 |
| ISO 13485 | Quality management system | 2016, reconfirmed October 31, 2025 | Incorporated into FDA’s QMSR since February 2, 2026 |
| IEC 81001-5-1, AAMI SW96, AAMI TIR57 | Security for health software and devices | 2021, 2023, 2016 (R2023) | All FDA-recognized; TIR57 and SW96 are cited in the February 2026 cybersecurity guidance |
How devices reach the US market
| Fact | Number | Source |
|---|---|---|
| Product codes in FDA’s classification database | 7,094: 34% Class I, 51% Class II, 7% Class III | openFDA query run October 9, 2026 |
| Class I product codes exempt from 510(k) | 2,155 of 2,403 (90%) | openFDA query run October 9, 2026 |
| Class II product codes that need a 510(k) | 3,004 of 3,644 (82%) | openFDA query run October 9, 2026 |
| Positive original FDA decisions in FY2025 | 3,245 510(k) clearances (98%), 30 De Novo grants, 38 original PMA approvals | openFDA query run October 9, 2026 |
| 510(k)s cleared in calendar 2025 | 3,198, of which 83% Traditional and 15% Special | openFDA query run October 9, 2026 |
| Average total time to a 510(k) decision, FY2025 cohort | 141 days | FDA MDUFA quarterly report, Q3 FY2026 |
What we do not do
- Regulatory strategy and submissions. We prepare the engineering side: design history file, risk management inputs, verification reports and documentation for the 510(k) or De Novo package. The strategy and the submission stay with you or your regulatory consultant.
- Clinical study management. We supply study devices and software, contribute to the technical parts of the protocol, support the study and analyze the results; the sponsor and the clinical team run it.
- Volume manufacturing. We build prototypes, golden samples and batches of up to 200 units. Volume production goes to a contract manufacturer, and we support the transfer.
We are not consultants or advisors. We are engineers who are ready to take full responsibility.
Questions
How much does it cost to develop a medical device?
It depends on scope more than on device class. In Lisa Voronkova’s breakdown, a small project takes 2,000 to 3,000 engineering hours, a mid-size one 5,000 to 6,000, and large programs such as ventilators or glucose monitors 10,000 to 30,000. At $125 per hour that is about $250,000 to $375,000, $625,000 to $750,000, and $1.25 million and up. Design for manufacturing adds 2,500 to 4,000 hours for an average product.
How long does development take?
Lisa describes small projects as half a year to a year, mid-size projects as about a year with the team fully loaded, and large programs as 12 to 16 months and more before clinical and regulatory work. One of our post-operative cold therapy devices went from concept to clinical trials in 12 months.
Do you handle FDA submissions?
No. We prepare the engineering side of the submission: design history file, risk management inputs, verification reports and the technical documentation. The regulatory strategy and the submission stay with you or your regulatory consultant.
Can you manufacture the device?
We build prototypes, golden samples and pilot or clinical batches of up to 200 units in house. For volume production we prepare the design transfer and work with the contract manufacturer you choose, in the United States, Europe or Asia.
Is your quality system certified?
Yes. The group’s quality management system is certified to ISO 13485:2016: certificate 044-25, held by Canyon Medical Inc., valid to October 13, 2028, for design and development, production and distribution of medical device prototypes. Details: our quality system.
Where is the engineering team?
Most of our engineers work in Ukraine. We also have offices in New York, Florida, the United Kingdom and Estonia. Our clients mostly target the US market, and we work to US expectations for documentation and delivery.
Do you fix your own mistakes at your cost?
Yes. If something we designed does not work as specified, we fix it at our cost.
Related pages
Tell us what your device has to do
A short call with an engineer is usually enough to see the main technical risks and what the first phase should cover.
Sources
- Lisa Voronkova on the Global Medical Device Podcast, September 2026 (project sizes, two project budgets, golden sample, design for manufacturing)
- Lisa Voronkova at the Grant Engine roundtable, July 2025
- Lisa Voronkova on BoneChat, June 2026 (share of wearable projects)
- Engineering note: the ten-board portable ventilator
- OVA Solutions quality system and ISO 13485:2016 certificate
- IEC 60601-1 Edition 3.2
- IEC 62304 Edition 1.1
- ISO 10993-1:2025
- ISO 13485:2016
- FDA recognized consensus standards database
- openFDA device APIs (classification, 510(k), PMA)
- FDA MDUFA quarterly performance report, Q3 FY2026
- 21 CFR 820.10
Updated on October 9, 2026.